
Last updated: October 29, 2026
Key Takeaways
- Home healthcare starts with a discharge handoff, not the first house call.
- The discharge care plan should guide the first 7 to 14 days at home.
- Scheduled visits, clear orders, and shared records help home healthcare work after discharge.
- Medication changes after discharge are a common source of problems at home.
Post-discharge home care is the support that starts when a person leaves the hospital but still needs help at home with medicine, wounds, rehab, or daily routines. The key question is not “what is home healthcare?” but “what happens next, in what order, and who does what?” This article explains how home healthcare works after a hospital discharge, and that transition is usually managed by the hospital discharge planner, then carried out by a home health nurse, a physical therapist, and the patient’s primary care physician.
What home healthcare does in the first 24 to 72 hours
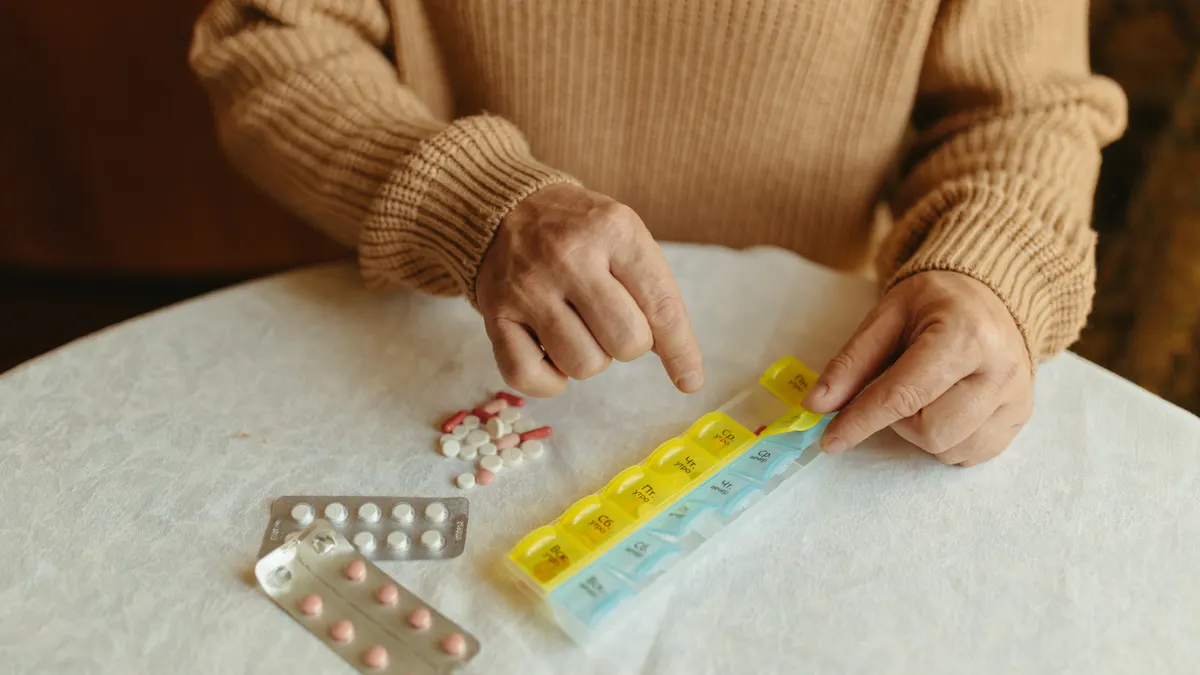
Home healthcare after hospital discharge begins with a handoff, not with a house call. The hospital discharge planner sends the care plan, medication list, diagnosis summary, and any wound or therapy instructions to the home health agency and the primary care physician. From there, the first 1 to 3 days usually focus on safety: getting the patient home, checking whether the instructions make sense, and confirming what needs to happen before the next follow-up visit.
The first visit is often by a home health nurse. That visit can include a medication reconciliation, a wound check, vital signs, and a review of the discharge instructions. If rehab is part of the plan, a physical therapist may follow with mobility work, such as walking practice, transfer training, or exercises tied to the hospital’s orders. If the patient has a new drain, dressing, oxygen setup, or mobility aid, the home team checks that those items are being used correctly.
The first few days matter because hospital discharge instructions are often written for a busy ward, not a kitchen table. A family member may be looking at 8 pages of paperwork, three new prescriptions, and a follow-up appointment that needs to be booked before the week ends. The home team’s job is to turn that stack of paper into a workable routine.
A typical first-week flow looks like this:
- Confirm the discharge packet before leaving the hospital. Ask for the medication list, wound instructions, therapy orders, and follow-up dates in one packet. The result is fewer gaps once the patient gets home.
- Set up the home space on day 0 or day 1. Put medications, a thermometer, a phone charger, clean linens, and any walker or cane within reach. The result is less scrambling during the first night.
- Receive the nurse’s first visit within the first few days if ordered. The nurse reviews symptoms, medicines, and any red flags. The result is a clearer picture of whether recovery is on track.
- Start therapy on the schedule ordered by the physician. The physical therapist may begin with short sessions and simple exercises. The result is safer movement without overdoing it.
- Book the first outpatient follow-up before the week is over. The primary care physician or specialist should know the patient is home and what changed in the hospital. The result is continuity, not a reset.
For a broader definition of the service itself, the hub page on what is home healthcare belongs upstream of this one. For related discharge planning details, see hospital discharge planning and medication reconciliation.
The discharge care plan is the roadmap, not the paperwork
The discharge care plan is the roadmap because it tells the family who does what, when, and what to watch for over the next 7 to 14 days. A generic summary is not enough. A useful care plan names the diagnosis, lists every medication with dose and timing, states whether the patient needs home nursing or physical therapy, and spells out any wound care or equipment instructions.
A strong plan usually includes these pieces:
- Diagnosis and reason for admission. This helps the family understand what problem the hospital treated. If the wording is unclear, ask the discharge planner, nurse, or another qualified professional to explain it.
- Current medication list. New prescriptions, stopped medications, and changed doses should all be on one list.
- Activity limits. This may include weight-bearing rules, lifting limits, or whether stairs are safe.
- Wound or incision instructions. The plan should say how often to change dressings and what the wound should look like.
- Follow-up appointments. The plan should name the doctor, specialty, and time window.
- Warning signs. Fever, swelling, confusion, shortness of breath, or drainage changes should be clearly listed.
- Home services ordered. This is where home nursing, physical therapy, or occupational therapy appears.
One common mistake is treating the discharge packet like a receipt and leaving it untouched in a bag. If anything in the packet seems unclear, a discharge planner, nurse, pharmacist, or other qualified professional should review it. That costs time later, because home health staff will ask questions that the family cannot answer. The better move is to sit down for 10 to 15 minutes and mark the page with the medication schedule, wound steps, and appointment dates.
This is also where families should ask for plain language. “Take one capsule twice daily” is better than a scribbled note that says “BID.” “Change dressing every other day” is better than a loose reference to the surgeon’s instructions. If the packet seems inconsistent, the discharge planner or bedside nurse should clarify it before the patient leaves.
A discharge plan is not the same as a long-term care plan. It covers the transition period after hospitalization, usually the first days and weeks. It does not answer every question about recovery, but it gives the home team enough structure to start. If the plan is missing a medication change or a follow-up date, the risk is simple: the family guesses, and guessing with a fresh hospital discharge is a poor trade.
How home healthcare works after a hospital discharge?

Home healthcare works after a hospital discharge through scheduled visits, clear orders, and a shared record of what the patient needs at home. The hospital writes the orders, the home health agency carries them out, and the primary care physician stays in the loop for ongoing medical oversight. That arrangement only functions well when the family knows which person handles which task.
The division is usually practical:
- Hospital discharge planner: assembles the discharge instructions, referrals, and service orders.
- Home health nurse: checks the patient’s condition, teaches medication routines, monitors wounds, and reports concerns.
- Physical therapist: works on walking, transfers, balance, and strength after surgery, stroke, or another mobility-related admission.
- Primary care physician: reviews the bigger picture, renews long-term medications, and handles follow-up after the hospital episode.
The home health visit is not a mini-hospital stay. It is usually brief and targeted. The nurse may inspect an incision, ask about pain, take blood pressure, and review whether the patient took all medications correctly since the last visit. The physical therapist may spend the visit on stairs, a walker, or a set of home exercises. If the patient’s condition changes, the home team relays that information back to the physician.
There are limits. Home healthcare does not replace emergency care, and it does not mean a nurse is present all day. If a patient needs constant monitoring, frequent injections, or complex respiratory support that the home cannot safely manage, the discharge plan may need to change. That is why “home” is not automatically the right next step for every person leaving the hospital.
Overall, the most useful mindset is to treat the first week as a relay race. The hospital hands off information, the home team carries the next leg, and the family keeps the schedule from slipping. When that relay breaks, the first failure is usually small: a missed dose, a wet dressing left too long, or a therapy visit that never gets confirmed. Those small failures are what the process is designed to catch early. For more on discharge handoffs, see care transitions.
Medication management is where families avoid the most trouble
Medication management is where most discharge problems show up, because the home list often changes the day the patient leaves the hospital. A patient may come home with a new antibiotic, a pain medicine, a blood thinner, or a dose change to a long-term drug that was fine in the hospital but no longer matches the old bottle in the kitchen cabinet.
A practical approach is to work from one master list, if possible, and confirm it with the nurse or pharmacist. The list should show the drug name, dose, time of day, and purpose if possible. The home health nurse can often help reconcile what was prescribed at discharge with what is already in the home. That step matters because two bottles with similar names can be easy to confuse, especially if the patient is tired or in pain.
A few practical points make the difference:
- Keep the discharge list next to the medicine bottles, not in another room.
- Remove old bottles that no longer match the current instructions.
- Use a pill organizer only after the nurse or pharmacist confirms the timing.
- Ask about food rules, since some drugs need to be taken with meals and others do not.
- Ask what to do about a missed dose before the problem happens.
The trade-off is that medication management takes time on day 1, but it saves time later. If the family skips the review, the cost can be double dosing, omitted doses, or taking an old medication that the hospital meant to stop. That is not a small paperwork error; it can send the patient back to the emergency department.
The primary care physician should receive the updated list, especially if the patient has diabetes, heart disease, kidney disease, or takes more than a few long-term medications. That does not mean every question needs an immediate appointment. It does mean the post-discharge medication plan should not live only in the discharge folder. A readable list on the fridge or in a notebook is far better than a memory test after a long hospital stay. For medication safety guidance, see medication safety, pharmacist counseling, and the FDA’s medication resources.
Wound care and rehab at home need different kinds of attention
Wound care and rehab at home need different schedules, different tools, and different people watching them. A wound may need daily or every-other-day dressing changes, while rehab may happen 2 or 3 times a week plus short exercises on the days in between. Mixing those two jobs together leads to mistakes, because one is about cleanliness and healing, while the other is about movement and function.
For wound care, the home health nurse usually checks the incision or dressing site, cleans it if ordered, and teaches the family how to watch for changes. A good routine includes clean hands, the right dressing supplies, and a clear plan for disposal. The family should know whether the wound should stay dry, whether bathing is allowed, and what drainage is expected versus concerning. The point is not to turn a family member into a nurse; it is to make sure the wound is handled the same way every time.
For rehab at home, the physical therapist usually starts with the patient’s actual surroundings: the bed, the bathroom, the hallway, and the stairs. A walker may fit better than a cane for the first stage. A chair with arms may be easier for transfers than a low sofa. The therapist may assign exercises that take only a few minutes but need to be done correctly. If the patient pushes too hard too soon, soreness can turn into a setback. If the patient does too little, strength and confidence fade.
Common mistakes here include using the wrong dressing supplies, letting exercises pile up into one long session, or assuming pain means the rehab plan should stop. The better choice is to follow the written order and report changes. If the wound gets redder, warmer, or starts draining in a new way, that is a call to the nurse or physician. If rehab causes dizziness, chest pain, or a new inability to bear weight, that is not a “walk it off” problem. For more on wound care, see wound dressing changes and physical therapy at home.
What families should do before the first home visit
Families should prepare the space, the paperwork, and the questions before the first home visit. A 15-minute setup before the nurse arrives can prevent an hour of confusion later.
Start with the physical setup. Clear a path to the bed, bathroom, and kitchen. Put the walker, cane, or other device where the patient can reach it safely. Set out a table or counter space for medications, dressing supplies, a pen, and the discharge packet. If the patient uses a blood pressure cuff, thermometer, or scale, place those together in one visible spot.
Then gather the information the home team will need. That usually includes the discharge paperwork, insurance cards if they are needed for verification, contact numbers for the hospital team, and the current medication bottles. If someone else is helping, make sure that person knows the schedule for the first 3 to 5 days. One family member should be the main point of contact so messages do not get split across three phones.
Use the first visit to ask specific questions:
- Which symptoms mean I should call the nurse today?
- Which medication was changed, stopped, or added?
- How often should the wound dressing be changed?
- What should the physical therapy exercises look like at home?
- Which appointment has to happen first: primary care or specialist?
The biggest mistake is assuming the first visit will answer every question automatically. It will not. The visit works best when the family arrives with the packet, the medicines, and a short list of concerns. That lets the nurse or therapist spend time on the details that matter most instead of hunting for missing information.
This step is where families can also link the hospital discharge plan to the outpatient world. The primary care physician is the anchor if follow-up is needed beyond the immediate recovery period. If a specialist appointment was ordered, it should be written on the calendar before the first week is over, not left to memory. For appointment planning, see follow-up care.
When to call the nurse or doctor instead of waiting
Families should call the home health nurse or primary care physician when something changes that was not part of the discharge plan. A fever, a wound that looks worse, a medication reaction, or confusion that is new after discharge should not wait for the next routine visit.
Some examples are straightforward:
- The patient cannot keep medications down.
- A dressing is soaked through sooner than expected.
- The incision is increasingly red, swollen, or painful.
- Shortness of breath, chest pain, or a major change in alertness appears.
- The patient suddenly cannot do a movement that was possible the day before.
The reason to call early is simple: home healthcare is built to catch problems before they become readmissions. Waiting for “the next appointment” can turn a manageable issue into a hospital return. If the problem feels urgent or severe, emergency care is the right move instead of a home visit.
This is not the right setup for a family that wants total medical coverage at home. It works best when the patient is stable enough to leave the hospital, but still needs close follow-up for a short period. If the discharge plan is unclear, or if the home environment cannot support the instructions, the family should say so before the patient leaves the hospital. A discharge that looks smooth on paper can fail quickly in a real kitchen, hallway, or bathroom.
Drafted with AI; not yet reviewed by a person.